








ニキビ治療の歴史は、長らく「炎症との戦い」でした。
抗菌薬でアクネ菌を抑え、
レチノイドで角化を調整し、
イソトレチノインで皮脂分泌を減らす。
しかし近年、レーザー医学は全く異なる方向へ進み始めています。それが、「皮脂腺そのものを物理学的に制御する」という発想です。
このスライドで示されている1726nm波長は、その象徴とも言える存在です。
レーザー医学では、どの組織に熱が入るかは“吸収スペクトル”によって決まります。従来の多くのレーザーは、水やヘモグロビン、メラニンをターゲットとしていました。しかし1726nm付近は、Sebum(皮脂)への吸収が相対的に高くなる極めて特殊な領域です。
つまり、「皮脂腺を選択的に加熱できる可能性」がある。
これはニキビ治療において大きな意味を持ちます。
なぜなら、ニキビの本質は単なるアクネ菌感染ではなく、
・皮脂分泌過剰
・毛包閉塞
・慢性炎症
・マイクロバイオーム変化
が重なった“毛包脂腺ユニット疾患”だからです。
1726nmは、アクネ菌を直接殺すのではなく、「皮脂腺の機能そのもの」に介入するという、新しい物理学的アプローチなのです。
特に重要なのが、TRT(Thermal Relaxation Time:熱緩和時間)の概念です。
皮脂腺だけを選択的に傷害するためには、周囲真皮へ熱が逃げる前に、適切なパルス幅でエネルギーを集中させなければならない。そのため1726nmデバイスでは、冷却システムとパルス設計が極めて重要になります。
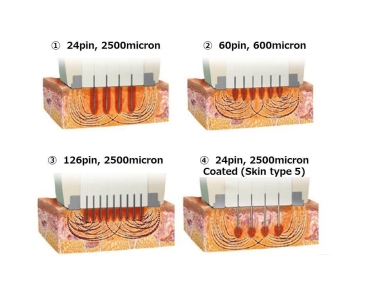
さらに下段に示されている「Multi-Wavelength Engineering」は、次世代デバイス設計の方向性そのものです。
従来は、「複数波長を重ねる」ことが進化だと思われていました。しかし現在は、“どこへ、どの波長を、どのチャネルで届けるか”を分離設計する方向へ進んでいます。
例えば1470nmや2940nmは深部蒸散や水加熱を担当し、1927nmは表層リモデリングを担当する。しかし重要なのは、「同じ空間へ熱を重ねない」ことです。
スライドにもあるように、水ターゲット型1927nmを別チャネル・別ポアへ分離することで、50℃を超える危険なBulk Heatingを避けながら、全層リモデリングを実現しようとしている。
つまり次世代レーザー医学は、
“強いエネルギーを一発で入れる”
時代ではなく、
“熱を精密に分配する”
時代へ入っているのです。
これはまさに、「エネルギー医学の半導体化」とも言える進化なのかもしれません。
Anderson RR, Parrish JA. Science. 1983;220(4596):524-527.
Paithankar DY et al. Lasers Surg Med. 2002;30(1):1-9.
Friedman PM et al. J Am Acad Dermatol. 2004;50(6):908-914.
Del Duca E et al. J Clin Aesthet Dermatol. 2023;16(4):28-36.

For many years, the history of acne treatment was essentially a battle against inflammation.
Antibiotics were used to suppress Cutibacterium acnes.
Retinoids were prescribed to normalize keratinization.
Isotretinoin reduced sebum production.
In recent years, however, laser medicine has begun moving in an entirely different direction: the concept of “physically controlling the sebaceous gland itself.”
The 1726nm wavelength shown in this slide is a symbolic example of that shift.
In laser medicine, the tissue that absorbs thermal energy is determined by its absorption spectrum. Traditionally, most lasers targeted water, hemoglobin, or melanin. Yet around 1726nm lies a highly unique spectral region in which absorption by sebum becomes relatively elevated.
In other words, there is potential for “selective heating of the sebaceous gland.”
This carries major implications for acne treatment.
Because acne is not simply a bacterial infection caused by C. acnes. Rather, it is a disease of the pilosebaceous unit involving the overlap of:
Excessive sebum production
Follicular obstruction
Chronic inflammation
Microbiome alterations
The 1726nm wavelength therefore represents a new physics-based approach—not by directly killing bacteria, but by intervening in sebaceous gland function itself.
Particularly important here is the concept of TRT (Thermal Relaxation Time).
To selectively damage sebaceous glands, energy must be delivered with an appropriate pulse duration before heat diffuses into the surrounding dermis. This is why cooling systems and pulse engineering become critically important in 1726nm devices.
The “Multi-Wavelength Engineering” shown in the lower section reflects the future direction of next-generation device design itself.
In the past, technological advancement was often equated with “stacking multiple wavelengths together.” Today, however, the field is moving toward a strategy of separating exactly:
Where energy is delivered
Which wavelength is used
Through which channel it is transmitted
For example, 1470nm and 2940nm wavelengths may handle deeper ablation and water heating, while 1927nm is assigned to superficial remodeling. The key principle, however, is avoiding thermal overlap within the same spatial zone.
As illustrated in the slide, separating water-targeting 1927nm energy into different channels or pores may allow full-thickness remodeling while avoiding dangerous bulk heating above 50°C.
In other words, next-generation laser medicine is no longer entering an era of:
“Delivering one massive burst of energy.”
Instead, it is entering an era of:
“Precisely distributing thermal energy.”
This evolution may ultimately resemble the “semiconductorization of energy medicine”—a transition from brute-force power toward exquisitely engineered precision.
Anderson RR, Parrish JA. Science. 1983;220(4596):524-527.
Paithankar DY et al. Lasers Surg Med. 2002;30(1):1-9.
Friedman PM et al. J Am Acad Dermatol. 2004;50(6):908-914.
Del Duca E et al. J Clin Aesthet Dermatol. 2023;16(4):28-36.